

Key Development
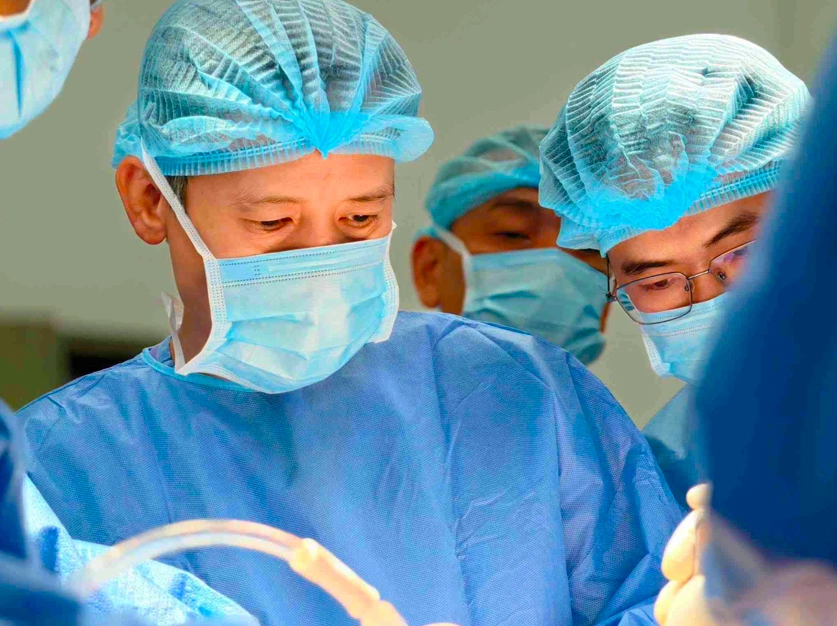
Viet Duc University Hospital has performed its first robot-assisted total knee replacement, marking another step in the adoption of digitally enabled orthopedic surgery at one of Vietnam’s major surgical centers.
The October 2, 2026 procedure involved a 68-year-old man with long-standing bilateral knee osteoarthritis who had failed conservative treatment. The robotic system supported patient-specific surgical planning, bone preparation and implant positioning, while the surgeon retained responsibility for diagnosis, operative strategy and intraoperative decisions.
The milestone matters because Viet Duc performs more than 50,000 orthopedic trauma and spine procedures annually and already lists minimally invasive arthroplasty, navigation and robotic techniques among its capabilities.
Why It Matters
- Robotics most consistently improves precision. A meta-analysis of 21 randomized trials involving 2,692 patients found significantly fewer mechanical-alignment outliers with robotic-assisted TKA.
- Greater precision has not consistently translated into better patient-reported outcomes. WOMAC and Oxford Knee Score differences remain limited across many studies.
- Operating time can increase. The same randomized-trial meta-analysis found robotic procedures were approximately 20 minutes longer on average.
- Economic value remains unsettled. A 2026 systematic review reported higher direct costs for robotic TKA while concluding that long-term survivorship and cost-utility remain insufficiently proven.
Healthcare Insight Analysis
Healthcare Insight believes the most strategically important feature of robotic knee replacement is not the robot itself.
It is the possibility of turning surgical craftsmanship into measurable data.
Conventional knee arthroplasty relies heavily on anatomical landmarks, mechanical guides and surgeon experience to determine bone cuts, implant rotation, alignment and soft-tissue balance.
Robotic systems introduce a different workflow:
anatomical mapping → patient-specific plan → intraoperative measurement → controlled bone preparation → implant positioning → outcome tracking.
Each step can potentially become measurable.
For a high-volume hospital, that creates something more valuable than a single precise operation: a learning system.
Hospitals can begin correlating exact alignment and balancing strategies with pain, function, rehabilitation speed, implant survival and revision.
That may ultimately be the stronger moat.
The current evidence, however, demands caution.
A 2026 meta-analysis covering 52 studies again found superior alignment accuracy with robotic TKA, but most patient-reported outcome differences remained small and long-term revision findings were inconsistent.
The evidence therefore currently looks like:
precision advantage: relatively clear.
durable patient-value advantage: still uncertain.
That distinction matters greatly in Vietnam.
Robotics introduces capital expenditure, maintenance, proprietary instruments or consumables, software, training and potentially longer operating-room time.
At low procedure volumes, fixed costs can make the technology difficult to justify economically.
A high-volume institution such as Viet Duc may have a stronger case because capital costs can be spread across more procedures, surgeon learning can occur faster and the platform can serve as a training infrastructure.
The correct KPI is therefore not:
“How many robotic systems does the hospital own?”
It is:
alignment outliers ↓ → complications/revisions ↓ → rehabilitation time ↓ → length of stay ↓ → implant survival ↑ → lifetime cost per successful joint ↓.
If that chain cannot be demonstrated, robotic surgery may remain technologically impressive without becoming economically superior.
The milestone also has implications for Vietnam’s medtech ecosystem.
Viet Duc surgeons have raised the possibility of eventually developing systems better suited to Vietnamese anatomy and patient affordability.
Localization, however, should not be viewed purely as building a domestic robotic arm.
The higher-value layers may include surgical planning software, anatomical datasets, navigation algorithms, servicing, training and outcome analytics.
In other words, robotics could create a new orthopedic technology stack rather than just another imported capital device.
Market Implications
Hospitals: high-volume centers are best positioned to justify robotic investment and generate outcome evidence.
Medtech companies: competition increasingly involves an ecosystem of robot + implant + software + maintenance + data.
Payers: premium reimbursement will be difficult to justify without evidence of lower revision, shorter stay or better lifetime value.
Surgeons: robotics does not remove expertise; it shifts expertise toward planning, interpretation and technology-enabled execution.
ANALYTICAL MATRIX
| Dimension | Current Evidence | Opportunity | Remaining Question |
| Precision | Relatively strong | Fewer alignment outliers | Does it improve durability? |
| Functional outcomes | Mixed | Better selected-patient recovery | Clinical significance |
| Economics | Higher upfront cost | High-volume utilization | Cost per case |
| Training | Standardized workflow | Faster knowledge transfer | Platform dependency |
| Vietnam | Early adoption | Local software/service ecosystem | Volume + reimbursement |
This first case should therefore be seen as the beginning of local evidence generation, not the end of the debate over robotic surgery.
If Viet Duc and other major centers build registries tracking alignment, PROMs, complications, revision, hospital stay and cost, Vietnam can answer the question that matters most using its own patients and health-system economics:
placing a knee implant more precisely is increasingly achievable; the harder question is whether that precision helps patients function better for long enough to justify the additional technology.
Source: https://vnexpress.net/benh-vien-viet-duc-lan-dau-thay-khop-goi-bang-robot-5127883.html